The pulmonary edema (OAP) is not limited to dyspnea with bilateral crackles. Several clinical presentations coexist, and the timeline of symptom onset directly modifies the management strategy. Here, we detail the semiological elements that allow for a rapid diagnosis, even in misleading presentations.
Gasometry and OAP: Initial respiratory alkalosis as a diagnostic trap
A common mistake is to exclude OAP in the presence of a minimally disturbed arterial gasometry. In early forms, the absence of initial hypoxemia does not exclude OAP. The patient hyperventilates to compensate for the beginning alveolar congestion, leading to respiratory alkalosis with low PaCO2 and high pH.
This phase can last from a few minutes to over an hour, depending on the speed of onset. The clinician who stops at this gasometric result risks delaying treatment. It is the shift towards respiratory acidosis that indicates ventilatory fatigue and worsening: PaCO2 rises, pH falls, and hypoxemia becomes evident.
We recommend never interpreting isolated gasometry without correlating it with the clinical examination and the kinetics of symptoms. Close gasometric monitoring (thirty to sixty minutes) allows for capturing this transition, which constitutes an immediate severity criterion directing towards assisted ventilation. To better understand the clinical signs of OAP in medicine, this gas dynamic should be integrated into the reasoning from the time of admission.

Cardiac asthma and wheezing: Distinguishing OAP from COPD decompensation
Wheezing associated with OAP remains one of the most frequent diagnostic traps in emergency medicine. A bronchospasm due to pulmonary congestion mimics asthma or a COPD exacerbation, and the isolated administration of bronchodilators without addressing the overload delays cardiac management.
The term cardiac asthma precisely refers to this picture. Several elements point towards a cardiac rather than bronchial origin:
- The orthopneic position is almost constant in OAP, while it is variable in decompensated COPD without a cardiac component
- Bilateral crackles predominant at the bases accompany wheezing, which is unusual in pure asthma
- Signs of systemic venous congestion (jugular distention, hepatojugular reflux, lower limb edema) indicate decompensated left heart failure
- The known cardiac context (ischemic heart disease, valvular disease, rapid atrial fibrillation) reinforces the hypothesis of OAP
In the COPD patient with known heart disease, both mechanisms frequently coexist. We observe that the response to intravenous diuretics in the first few minutes constitutes a useful therapeutic test: a rapid improvement in dyspnea and wheezing strongly points towards the congestive component.
Signs of low output associated with OAP: When congestion masks shock
Signs of low output should be systematically sought, even when respiratory distress dominates the picture. Tachycardia, weak pulse, profuse sweating, pallor, cold extremities, and oliguria indicate insufficient systemic perfusion. Their presence radically changes the therapeutic strategy.
An OAP with signs of low output points towards cardiogenic shock or OAP due to severe systolic dysfunction. In this case, intravenous nitrates, usually first-line treatment, must be used with caution due to the risk of hypotension. The priority shifts towards inotropic support and close hemodynamic monitoring.
Rapid clinical assessment at the patient’s bedside
The examination is structured around two simultaneous axes: congestion and perfusion. A “warm and wet” patient (well perfused but congested) requires vasodilators and diuretics. A “cold and wet” patient (poorly perfused and congested) necessitates a different approach, often involving inotropes.
The systolic blood pressure at admission is the pivotal parameter for this orientation. A preserved pressure allows for nitrates at titrated doses. A low pressure necessitates reconsidering the entire therapeutic scheme even before biological results are available.
Flash OAP: Recognizing the rapid onset as a diagnostic criterion
Flash OAP is characterized by its rapid onset, sometimes within minutes. The patient transitions from a stable respiratory state to major distress with orthopnea, diffuse bilateral crackles, and pink frothy sputum. The abrupt nature is the distinguishing element, as there are no specific numerical criteria that separate it from classic acute cardiogenic OAP.
The most common etiologies of flash OAP include severe hypertensive crisis, mitral chord rupture, and acute myocardial ischemia. The common point is a sudden increase in left ventricular filling pressure, with rapid movement of plasma fluid from the capillaries to the alveoli.
Chest X-ray in flash OAP
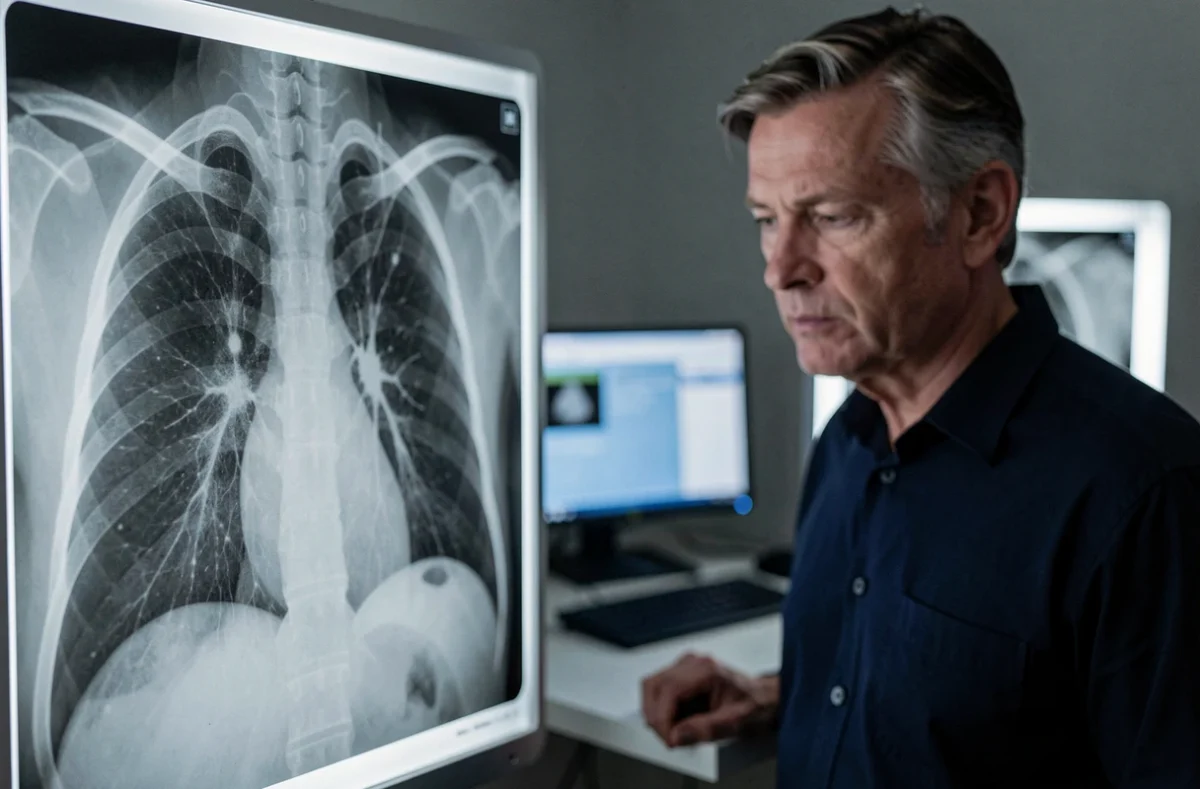
The chest X-ray may show a bilateral alveolar edema appearance resembling butterfly wings, but in very acute forms, imaging may lag behind the clinical picture. We sometimes observe a delay of several hours between the onset of clinical signs and their complete radiological translation. A normal chest X-ray in the first few minutes should not rule out the diagnosis if the clinical picture is suggestive.
Pulmonary ultrasound at the patient’s bedside, searching for diffuse bilateral B lines, offers a more timely and sensitive alternative than standard X-ray in this emergency context. It also allows for the assessment of left ventricular function and the search for associated pericardial or pleural effusion.
The rapid recognition of OAP relies on integrating the kinetics of symptoms, a complete physical examination (congestion and perfusion), and sequential gasometry. The most time-consuming error remains treating wheezing as an isolated bronchospasm or reassuring based on an initially falsely normal gasometry.


